
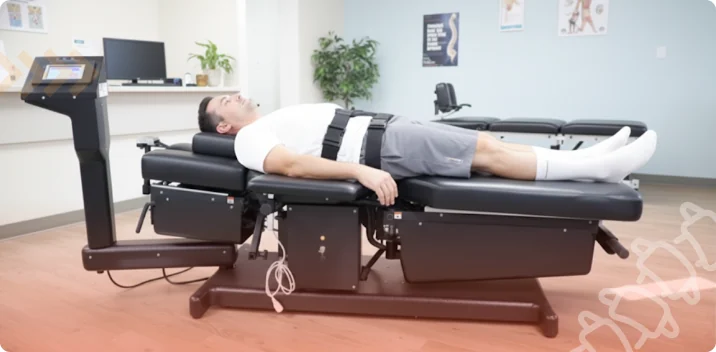
There is a moment when back pain stops sounding like back pain. The ache moves. It runs into a buttock, down a thigh, past the knee. Other symptoms arrive with it: pins and needles in the foot, a burning stripe along the calf, a leg that feels unreliable on stairs. That is a different problem from a sore back, and it needs a different plan.
Spinal decompression is the non-surgical option most people find when they search that pattern. The idea is simple: lower the pressure across an irritated segment, give the nerve a little more room, and use that window to rebuild tolerance. Whether it belongs in your plan depends on what your exam shows. That is worth understanding before you book computer-guided traction on a decompression table anywhere.
How Do You Know Disc Pressure Is Driving Your Symptoms?
Three things raise the suspicion together. Pain that travels into a limb rather than staying local. Symptoms that change sharply with position. Sensory changes such as tingling, numbness or burning. One of those on its own means little. All three in the same story means something.
Mayo Clinic describes a herniated disk as the softer inner material pushing through the tougher outer ring. That is where it can press on a nerve and produce pain, numbness or weakness along that nerve's path. That is why where you feel the numbness matters so much. The spot that tingles says more about which level of your spine is involved than the spot that aches does.
Position is the second clue. Long sitting, driving and forward bending load a lumbar disc, so symptoms that spike during a commute and ease after a walk fit the pattern. Symptoms that feel identical no matter what you do usually do not.
What Does Non-Surgical Spinal Decompression Do?
A decompression table applies controlled, cyclical traction along the length of the spine. The intent is to reduce compressive load across the targeted segment for a set period. That creates a short window where the pressure around the disc and the nerve root is lower than your ordinary day allows.
The most useful evidence comes from a randomized study in subacute lumbar disc herniation. Non-surgical decompression produced greater leg pain reduction and measurable shrinkage of herniated disc volume on follow-up imaging than the control group did. That is a real finding on a real outcome. It is also one study in a selected group of patients, and it should be read that way.
There is a second effect that gets less attention. When a segment stops feeling threatened, the muscles bracing around it often stop working so hard. Less guarding means smoother movement, and smoother movement is what lets rehabilitation begin.
Which Symptoms Suggest a Good Match, and Which Do Not?
Decompression is usually considered when the exam points to a bulging or herniated disc pressing on a nerve root. That means pain traveling into a limb, symptoms that change with position, and sensory changes. It also means a story that has not settled with time and simple measures.
It is a poorer match when your symptoms point elsewhere. Pain that stays local and mechanical, joint-driven pain with no neurological signs, and symptoms that behave identically in every position all suggest a different cause. So does a history of severe instability, significant osteoporosis, prior fusion hardware or an active fracture. Each of those needs its own conversation first.
Most disc herniations improve without surgery. StatPearls notes that the prognosis for lumbar disc herniation is generally favorable with conservative management, with many patients improving over weeks. That is reassuring, and it is also the reason to be picky. Conservative care has room to work, so it is worth aiming correctly.
When to See a Doctor Right Away
Some symptoms need a physician the same day rather than any conservative plan. If you notice loss of bowel or bladder control, numbness across the saddle area, or a leg getting weaker quickly, seek medical care first. The same goes for significant trauma, fever alongside severe spine pain, or unexplained weight loss with new back pain.
Those are the recognized warning signs in clinical practice. StatPearls lists saddle anesthesia, new bladder dysfunction and progressive neurological deficit among the warning signs that change the pathway entirely.
Nobody at a chiropractic office should be selling you a course of care when your story contains one of those. We screen for them at intake for exactly that reason, and a same-day referral is the right outcome when one appears.
What the First Weeks of a Decompression Plan Look Like
The plan starts with the exam findings, not with the table. We check range of motion, the positions that reproduce your symptoms, and a neurological screen covering strength, reflexes and sensation. We also take an honest look at what your day demands of your spine.
From there, table settings are chosen for your presentation and your tolerance, then adjusted based on how you respond between visits. Progress gets tracked by things you can verify. How far the symptom travels down the leg. How long you can sit before it changes. Whether you sleep through the night. Those markers tell you more than a pain score on its own.
The table is rarely the whole plan. It usually runs alongside the disc and nerve rehabilitation programs that support it. Pressure relief buys a window, and movement work is what turns that window into lasting tolerance.
Does Decompression Work Better Than Waiting It Out?
For some people, no. Many disc-related symptoms settle with time, sensible movement and patience, and someone in that group would improve either way. We will tell you if that sounds like you rather than sell you a course of care.
The group that benefits most is the one that has already waited. Months of symptoms, a clear nerve pattern, activities you have dropped, and no sign of steady improvement. For those patients, structured pressure relief plus graded rehabilitation is a reasonable non-surgical option before anyone starts discussing injections or surgery.
If a course of care produces nothing you can measure, that is information too. A plan that is not working should change rather than repeat, and we will tell you.
There is one more reason not to simply wait. Symptoms that have been running for months change what you do. You stop lifting, you stop walking as far, you sit differently, you sleep worse. Those changes outlast the original irritation and become their own problem. Treating the disc while you rebuild the activity you dropped is what keeps a nerve episode from permanently shrinking your week.
How to Find Out If Decompression Fits You
Nerve-pattern symptoms make people cautious about ordinary things. Sitting through a film, bending to load the dishwasher, driving to Lady Lake and back. That caution is rational, and it also costs you one habit at a time.
A useful plan starts by confirming what is driving the pattern. Then it matches the tools to that, and measures whether they are working. Dr. Justin Bergin, DC, will tell you when decompression fits your symptoms and when it does not. Bring your symptom map and your timeline, and ask whether decompression suits your presentation at the Lakeland or Lady Lake office.
Ready to take the next step?
Talk with the ChiroMed team about a spinal decompression plan built around what your examination actually finds.